Pain is not a neat signs and symptom. It shows up split with worry, culture, assumption, and physiology that rarely behaves like a book. PUAEME008 Offer Discomfort Administration rests at that junction of science and judgment, where the clinician needs to evaluate swiftly, treat safely, and reassess without one-track mind. This device is extensively made use of in prehospital and severe care contexts, throughout ambulance, very first responder, remote wellness, and occasion medicine roles. It pairs well with pain management courses for nurses and pain administration programs for physiotherapists who work in immediate or field environments, and it creates a component of several brief courses in pain management aimed at constructing sensible ability rather than academic breadth.
This article focuses on just how the principles within PUAEME008 play out under stress. The complying with scenarios and case studies show usual predicaments, sensible timelines, and the type of compromises that figure out whether your patient obtains relief without excessive risk.
What the unit anticipates you to do well
PUAEME008 Supply Discomfort Management requires more than familiarity with analgesic alternatives. It anticipates you to:
- Recognize pain without delay, evaluate it suitably for the individual, and screen for trends. Balance medicinal and non-pharmacological strategies. Apply drugs from your range of practice safely, with the best signs, doses, and route. Anticipate unfavorable events, particularly respiratory system clinical depression, hypotension, oversedation, and medication interactions. Communicate clearly, consisting of informed permission, explanation of alternatives, and handover to getting clinicians.
That collection of assumptions underpins numerous a discomfort administration certification training course. A great pain monitoring accreditation course highlights decision production as much as pharmacology. In technique, the judgment calls issue most.
The first 5 mins: evaluation that acquires you time
When discomfort is intense and extreme, the temptation is to grab the fastest-acting treatment. In some cases that is right, sometimes it develops blind spots. An organized technique makes you faster and safer:
- Get the basics in position: respiratory tract, breathing, blood circulation, impairment, direct exposure. A missed out on stress pneumothorax or hemorrhage will not wait while you titrate analgesia. Use a discomfort scale the patient understands. Mathematical (0 to 10) benefits lots of adults. Faces ranges are handy for kids or patients with minimal English. In advanced dementia, rely on behavior cues and verified observational devices if available. Clarify system and warnings. Pain with brand-new neurological deficit, chest pain with diaphoresis, serious stomach discomfort with protecting, or discomfort after high-speed injury modifications your risk resistance and analgesic strategy. Start non-pharmacological procedures alongside your evaluation. Paralyze cracks, raise damaged arm or legs, trendy burns with running water for up to 20 mins, and provide tranquil, clear communication. These are not soft alternatives, they reduce nociceptive input and frequently reduced drug needs by a 3rd or more.
The style of evaluation explained over attributes highly hurting management training programs that line up with PUAEME008. It pulls you away from autopilot application and towards targeted care.
Scenario 1: The femur fracture at a rural motocross track
A 27-year-old cyclist lays on a dirt track, best leg shortened and on the surface turned. Vitals on arrival: HUMAN RESOURCES 112, BP 128/76, RR 20, SpO2 98 percent on room air, GCS 15. Discomfort rating 9 out of 10, intensified by any kind of motion. The event is 90 mins from the nearby hospital.
Judgment and sequence matter here. Initially, immobilize the arm or leg and use a grip splint if trained and shown. The mechanical decrease in activity frequently goes down discomfort by 2 to 3 factors within minutes. Next, select an analgesic plan that fits your extent. In lots of rescue services, breathed in methoxyflurane or titrated IV fentanyl are first-line alternatives for serious arm or leg pain. If you have IV access, little, regular dosages of fentanyl can titrate quickly with less histamine impacts than morphine. If IV gain access to is delayed or hard, methoxyflurane can bridge efficiently while you establish lines and plan for transport.
Two challenges recur in this setting. First, providing a huge solitary bolus of opioid in an individual whose bleeding threat stays unidentified. Although his vitals are steady, you must reassess for concealed injuries, especially if the accident included high-energy transfer. Second, overlooking antiemetics early. Throwing up in a supine, paralyzed client creates distress and aspiration danger. Providing an antiemetic with the first or 2nd opioid dosage often prevents a mess and a hazard.
Over the following hour, you will require to reassess repeatedly. Pain can spike with loading and discharging. Document the fad: 9 to 6 after traction, 6 to 4 complying with 50 micrograms fentanyl IV titrated over 5 minutes, secure vitals, no sedation. This kind of note tells the obtaining group what worked, just how much, and whether you saw adverse impacts. It is the sort of documents highlighted in any qualified offer pain management course.
Scenario 2: An upper body wall injury in an elderly fall
An 83-year-old slips in her yard and strikes her left breast on a block action. Currently she protects the location, breathing superficial, pulse 96, BP 148/84, RR 24, SpO2 94 percent, discomfort 8 out of 10 with deep breaths. She takes antihypertensives and an everyday anticoagulant for atrial fibrillation.
Chest wall surface discomfort in the senior provides a respiratory system cascade threat. Shallow breathing brings about atelectasis, which welcomes pneumonia within days. Getting her to take a breath successfully matters as much as comfort. Yet senior people likewise bring higher dangers with opioids: slower metabolism, sensitivity to sedation, and interaction with existing medications.
Non-opioid scaffolding assists. If within scope, think about paracetamol early at appropriate application and examine previous consumption to prevent cumulative overdose. NSAIDs can reduce swelling however ought to be stayed clear of or used cautiously in individuals with kidney problems, peptic abscess disease, or high blood loss threat, which prevails in this age group. Entonox can help temporary with movement, though it might be less efficient for prolonged control.
If an opioid is needed, begin low and go slow. Titrate fentanyl in smaller increments, observing breathing price and sedation ratings. Set analgesia with coaching and tools: splint the upper body with a folded towel during coughing and direct her with slow, deep breaths within her tolerance. Describe why a little discomfort in the brief ruptureds of breathing practice prevents larger problems later. Education and learning is an analgesic in its very own right, reducing fear-driven breath holding.
Many discomfort management programs for registered nurses highlight this circumstance because ward and neighborhood nurses commonly see the postponed effects. A pain monitoring certification that consists of senior care material will worry the equilibrium between ample relief and breathing vigilance.
Scenario 3: Shed pain that intensifies after the air conditioning stops
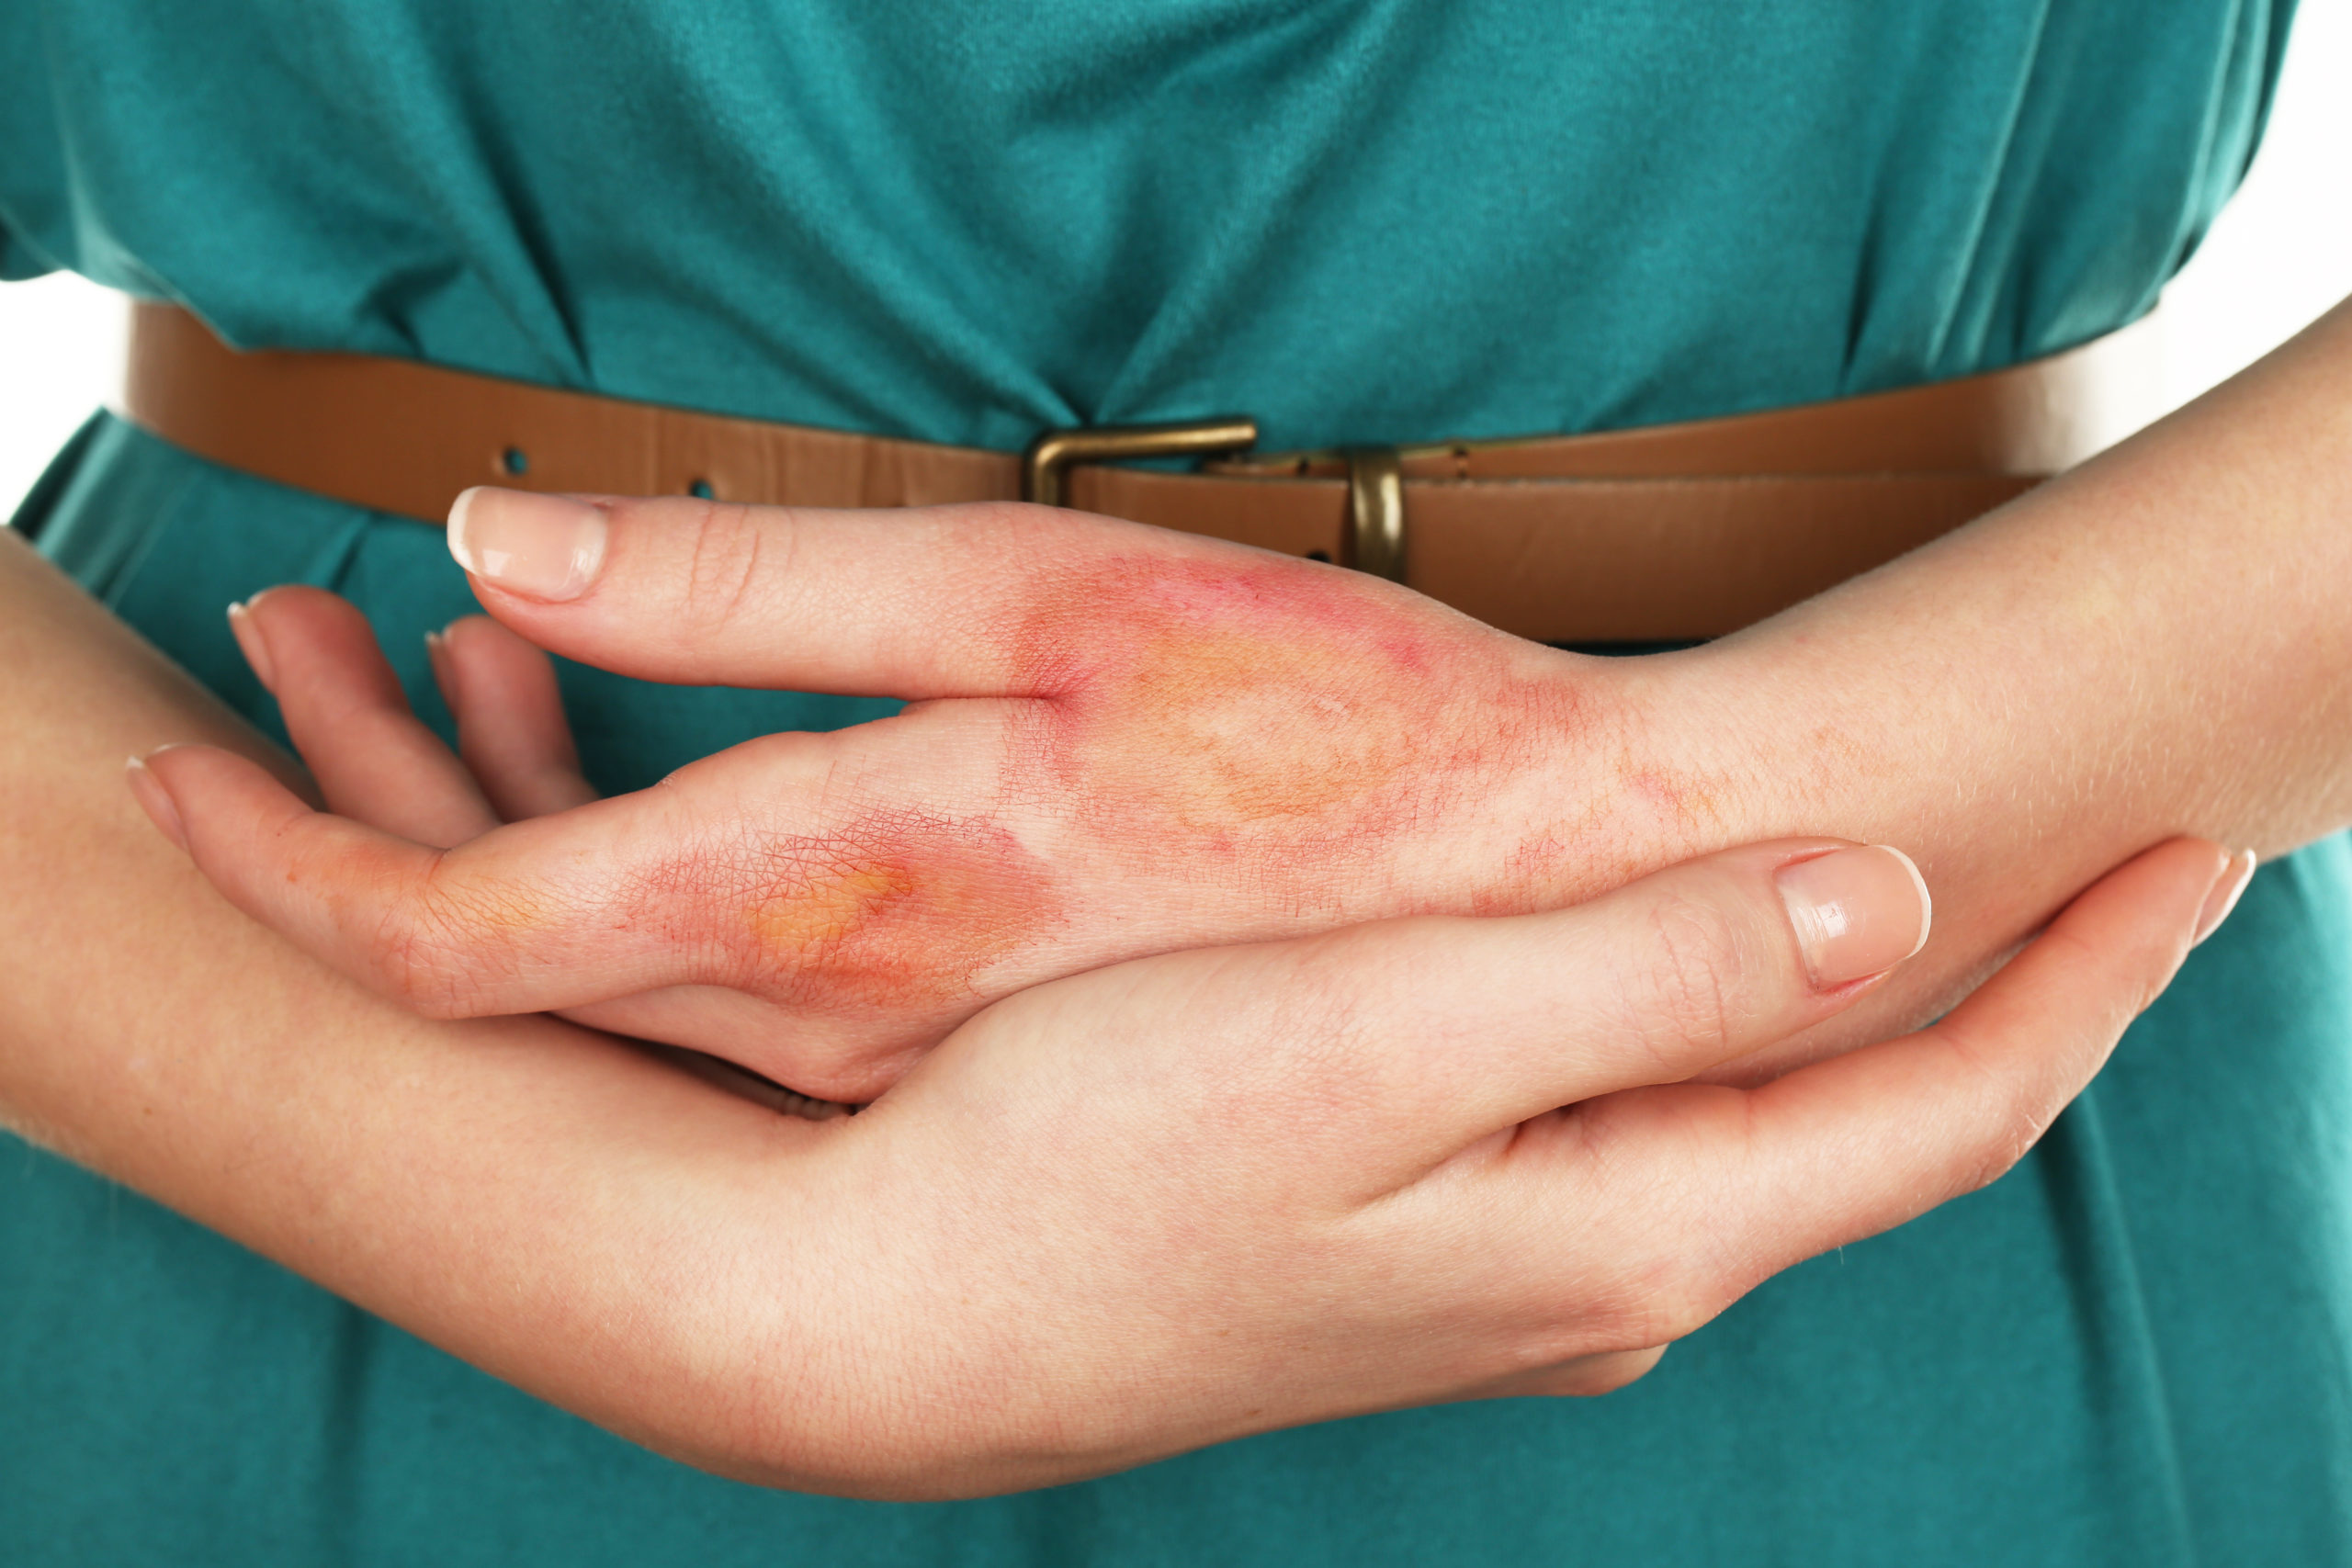
A 9-year-old touches a hot stove door with his forearm. Parents cooled down the melt under running tap water for 15 mins prior to you get here. The melt is superficial partial thickness with blistering over 6 percent of body surface area. His pain was a 7 during cooling, currently increasing to 9 as the water stops. He is distressed, declining touch.
Burn discomfort spikes when cooling down ends. The skin's nociceptors stay extremely active, and anxiousness escalates the experience. Reassurance alone does not suffice. If your scope includes intranasal fentanyl, it supplies quick, needle-free relief. It is especially helpful when IV access would be a battle in an anxious kid. Dosage meticulously based upon weight and reassess within mins. If methoxyflurane is offered and allowed for paediatric usage in your jurisdiction, it can give excellent procedural analgesia for clothing, with acquainted training: breathe gradually, take breaks if dizzy.
Cover the burn with an ideal dressing that will certainly not stick. Restricting additional exposure to air reduces pain. Maintain the youngster warm and stop hypothermia, a danger when air conditioning has been charitable. Kids wear away thermally faster than adults.
There is a common mistake in this circumstance: delaying analgesia up until after the very first dressing is applied. In practice, you want analgesia on board before you manipulate the wound. The distinction between a distressing very first dressing and a bearable one will shape every subsequent change. Pain monitoring training for nurses who staff emergency departments commonly consists of role-play around paediatric burns since the initial interaction establishes the tone for family members trust.
Scenario 4: The client with chronic opioid treatment and intense trauma
A 46-year-old contractor with a documented background of chronic reduced neck and back pain on lasting opioid therapy drops from a ladder and offers with a distal radius crack. He reports taking modified-release oxycodone 20 mg two times daily and immediate-release 5 mg up to three times a day. He is in serious pain, 10 out of 10, perspiring and light, and specifies that "the normal stuff will not touch this."
Tolerance makes complex regular dosing. The threat is twofold. If you underdose, you extend experiencing and trigger even more considerate anxiety. If you overcorrect without regard for his baseline tolerance and general direct exposure, you risk oversedation once the sharp pain subsides. Start by clarifying his last dosage and total daily morphine equivalent where feasible. After that strategy to titrate short-acting opioid in cautious increments while keeping track of sedation and respiratory rate very closely. Take into consideration accessories where within extent: ketamine at sub-dissociative dosages, nitrous oxide for brief procedural discomfort, or a regional method if you operate in a setting where nerve blocks are within your training and protocols.
In some systems, paramedics and progressed practitioners can make use of low-dose ketamine for severe sharp pain, particularly in opioid-tolerant people. It commonly decreases the total opioid demand and preserves respiratory tract reflexes when dosed thoroughly. Discuss negative effects openly, particularly dysphoria. A calmness, practical description goes a long means to stop panic if the experience feels odd.
This holds true that divides algorithmic application from genuine discomfort administration know-how. It is covered thoroughly in advanced pain management training courses, including certification program in pain monitoring programs that tackle complicated pharmacology, tolerance, and hyperalgesia.
Scenario 5: Abdominal pain where less is more
A 31-year-old presents with appropriate lower quadrant discomfort for 6 hours, gotten worse by movement, anorexia nervosa, mild fever. Vitals are secure. Scientific uncertainty for appendicitis is high. He desires solid discomfort relief now.
Older myths recommended withholding analgesia conceals the medical diagnosis. Evidence does not support that setting. Proper analgesia does not conceal peritonism or change the demand for imaging and surgical examination. Still, you select representatives that do not add confounders. Titrate opioid in small amounts with antiemetic cover and display response. pain management certification course Avoid NSAIDs if there is a risk of bleeding or kidney injury, though in stable clients with no contraindications, NSAIDs can decrease opioid need. Do not offer antispasmodics that may cloud the medical photo, unless guided by local protocol.

In emergency pain monitoring, the skill hinges on watching for modification. If pain and protecting instantly get worse, that matters greater than the absolute number on a range. Your reassessments lead urgency and transport priority.
Non-pharmacological levers that genuinely transform outcomes
Clinicians sometimes reject non-drug techniques as soft. In real-world technique, they commonly shift pain trajectories greater than another 10 micrograms of opioid would.
- Positioning: Elevate the injured limb for strains and fractures. Maintain the neck midline for cervical tenderness. Bend the hips slightly for peritoneal irritation. Little changes can drop pain scores rapidly. Immobilization: A well-applied splint changes bony pain. Reassess blood circulation, experience, and activity after application and at periods due to the fact that swelling evolves. Temperature inflection: Recurring trendy running water for thermal burns up to 20 mins limits depth and pain, yet prevent ice on acute bone and joint injuries beyond quick durations, as long term topping can enhance discomfort and harm cells perfusion. Quiet, clear description: Uncertainty and worry intensify discomfort understanding. A minute spent describing what you will certainly do, and what the client will certainly feel following, decreases catecholamines and reduces analgesic needs. Distraction and breathing: Guided breathing, straightforward checking, or concentrated methods audio low-tech and yet consistently aid in paediatric and nervous adult patients.
Well-designed pain administration training courses fold these components right into situations rather than listing them alone. They are part of the craft.
Dosing, paths, and the art of titration
Even with the very same drug, path matters. Intranasal shipment acquires gain access to when capillaries are scarce or time is short. IV titration allows finer control and faster offset. Dental routes rarely suit intense severe pain because of sluggish start and unpredictability in nauseated patients.
The principle that keeps medical professionals out of difficulty is titrate to result with frequent review. Provide the minimum effective increment, wait enough time to see the impact, then decide whether to add even more. Stay clear of stacking doses from representatives with overlapping respiratory downer effects within short windows, specifically benzodiazepines and opioids with each other, unless you are handling a certain sign with tracking and clear protocols.
Sedation scales and respiratory system rate fads are better than pulse oximetry alone. Pulse oximetry lags and can look fine till the patient tips right into hypoventilation. Matter respirations, look for air passage obstruction sounds, and prepare with basic respiratory tract maneuvers. In every discomfort administration qualification course that concentrates on prehospital care, teachers hammer these factors due to the fact that they protect against preventable harm.
Communicating threats, approval, and expectations
Patients want alleviation. They likewise intend to feel safe and notified. A short, clear discussion develops both. State what you suggest, why, the major risks in straightforward terms, and how you will look for them. With youngsters, include caretakers actively and structure choices in age-appropriate language. When English is limited, make use of interpreters where viable or verified interaction tools for pain scales. Record consent as part of your routine, not as a special case.
Handovers are an additional factor where pain administration either proceeds smoothly or derails. Include the baseline discomfort score, what you tried and in what doses, the patient's response, adverse impacts, and any non-pharmacological steps in place. If you began a titration strategy, say so. Smooth handover is as essential as the initial dose.
When the playbook modifications: cultural and trauma-informed care
Pain is infiltrated society and previous experiences. Some neighborhoods reduce verbal expression of suffering. Others use certain phrases to connect extent without numeric ranges. Attempt to match the person's design as opposed to forcing a rigid style. For patients with an injury history, sudden touch or crowded rooms can trigger dissociation or panic. Introduce your activities before you do them, ask for consent where possible, and provide the person some control, even if small, such as selecting which arm to use for monitoring.
These are not simply details. They impact analgesic demands, teamwork with procedures, and total outcomes. Programs that provide pain administration training for nurses significantly consist of trauma-informed structures due to the fact that they alter everyday practice.
The restraint trap: agitation and pain
Agitated people are often in discomfort. If you reach for physical restraint first, pain usually aggravates, agitation intensifies, and the danger of injury rises. Beginning by assuming pain is part of the image. Deal with likely resources while engaging verbally. If chemical sedation is required for security, titrate with agents that also provide analgesia when suitable, and remain to search for the underlying excruciating stimulation. It is surprisingly common to discover a missed out on fracture or dislocation when the individual settles.
Data you will really use: what to tape and why
Pain charts ought to narrate, not simply a number. The best documents pairs a score with context. "Pain 8 at remainder, 10 with movement, after splinting and 100 micrograms fentanyl collective IV now 3 at rest, 6 with activity, RR 16, sharp, no nausea or vomiting." That line lets an obtaining clinician continue titration wisely. For audits and for your very own discovering, it likewise offers a map of what worked.
In a pain management qualification program, particularly those designed as a pain management certificate for prehospital or event medical professionals, you will certainly typically be asked to send situation reflections. One of the most important reflections analyze timing, series, and monitoring, not just medication choice.
Where PUAEME008 fits within more comprehensive training
PUAEME008 Offer Pain Management typically appears together with injury and clinical emergency units, developing part of a package hurting administration training. For medical professionals constructing an occupation portfolio, a pain management certification complements broader certifications and sustains credentialing discussions with employers. If you currently hold a basic pain administration certification, this device adds the operational layer: quick assessment, short half-life representatives, step-by-step analgesia, and the technique of watching for issues in unchecked environments.

Providers supply various styles. Some market brief courses in pain management targeted to nurses in acute wards and access setups. Others customize discomfort administration training courses https://messiahxgzc813.image-perth.org/emergency-situation-pain-monitoring-quick-analysis-under-puaeme008 for physio therapists, focusing on subacute musculoskeletal pain, taping, activity methods, and non-opioid pharmacology awareness. When reviewing a give discomfort administration course, seek simulation time, scenario variety, local medicine procedures, and instructor experience. A training course loaded with lectures and thin on hands-on technique leaves gaps where it counts.
Case research reflections: 3 patterns that keep showing up
- Timing beats strength. Early, moderate analgesia plus good splinting commonly achieves far better outcomes than waiting and then delivering big dosages under stress. The second look is where you locate difficulty. After the first dosage or treatment, reassess with fresh eyes. Essential indications, discomfort quality, and reaction to movement can reveal missed out on injuries or evolving physiology. Teach while you treat. Explain what you are doing and why. People that comprehend the strategy work together better and record pain more accurately. That comments loophole improves your application and safety.
These patterns appear basic, yet in active scenes they are easy to fail to remember. Pain monitoring training embeds them through rep under different conditions.
Common risks and what to do instead
Many adverse occasions and suboptimal outcomes map back to a list of errors. 3 attract attention. Initially, ignoring the impact of non-pharmacological measures. Second, stacking sedatives. Third, anchoring on a solitary medical diagnosis when discomfort habits does not match the story. The alternative approach is basic to state and more challenging to practice: prioritize mechanical measures early, avoid consolidated respiratory depressants unless clearly suggested and monitored, and maintain checking your functioning medical diagnosis versus brand-new information.
Building confidence: method that counts
No training course changes repetition. If your service runs simulation days, volunteer for the pain stations. Technique intranasal delivery in a sensible timeline, IV titration while handling scene babble, and interacting with distressed family members. Ask instructors to add curveballs: a person that overreports discomfort, one who underreports, an unexpected drop in blood pressure after an opioid dosage. The point of a discomfort monitoring certification program is not just to pass evaluation, it is to build an internal library of patterns so you can respond comfortably when information shift.
Peer discussion increases knowing. After challenging calls, debrief particularly on pain choices. What would you alter next time? Would certainly earlier splinting have minimized dosing? Did we miss out on an antiemetic possibility? Did handover mirror the strategy? With time, these discussions raise the entire team's standard.
Final thought: relief with respect
Providing pain relief is both humane and clinical. The regard part indicates you soothe enduring without creating fresh risks, you listen to the person's language for discomfort, and you do not compel them right into your pace without explaining why. PUAEME008 Provide Discomfort Administration gives the scaffolding. Experience completes the spaces and polishes the judgment. Whether you are seeking a pain administration certificate, sampling brief training courses hurting administration to sharpen your edge, or embedding PUAEME008 offer pain administration within a wider ability structure, the goal is the same: exact assessment, effective relief, and alert follow-up. If you can provide those three under stress, the rest falls under place.